Genetic analysis questions obesity’s apparent survival benefit
In UK Biobank, a higher genetic score tracked higher death risk: the hazard ratio, a relative risk measure, was 1.05 per standard-deviation increase.
Mendelian randomization, dose-response
Limit: BMI is only a proxy for adiposity, limiting interpretation of its mortality associations
Edited by Boris Djordjevic · AgingResearch.News
An observational analysis examined 488,656 UK Biobank participants and 13,114 National Health and Nutrition Examination Survey participants. Researchers compared body mass index, a measure based on weight and height, with mortality across stages of cardiovascular-kidney-metabolic syndrome, which links heart, kidney and metabolic disease.
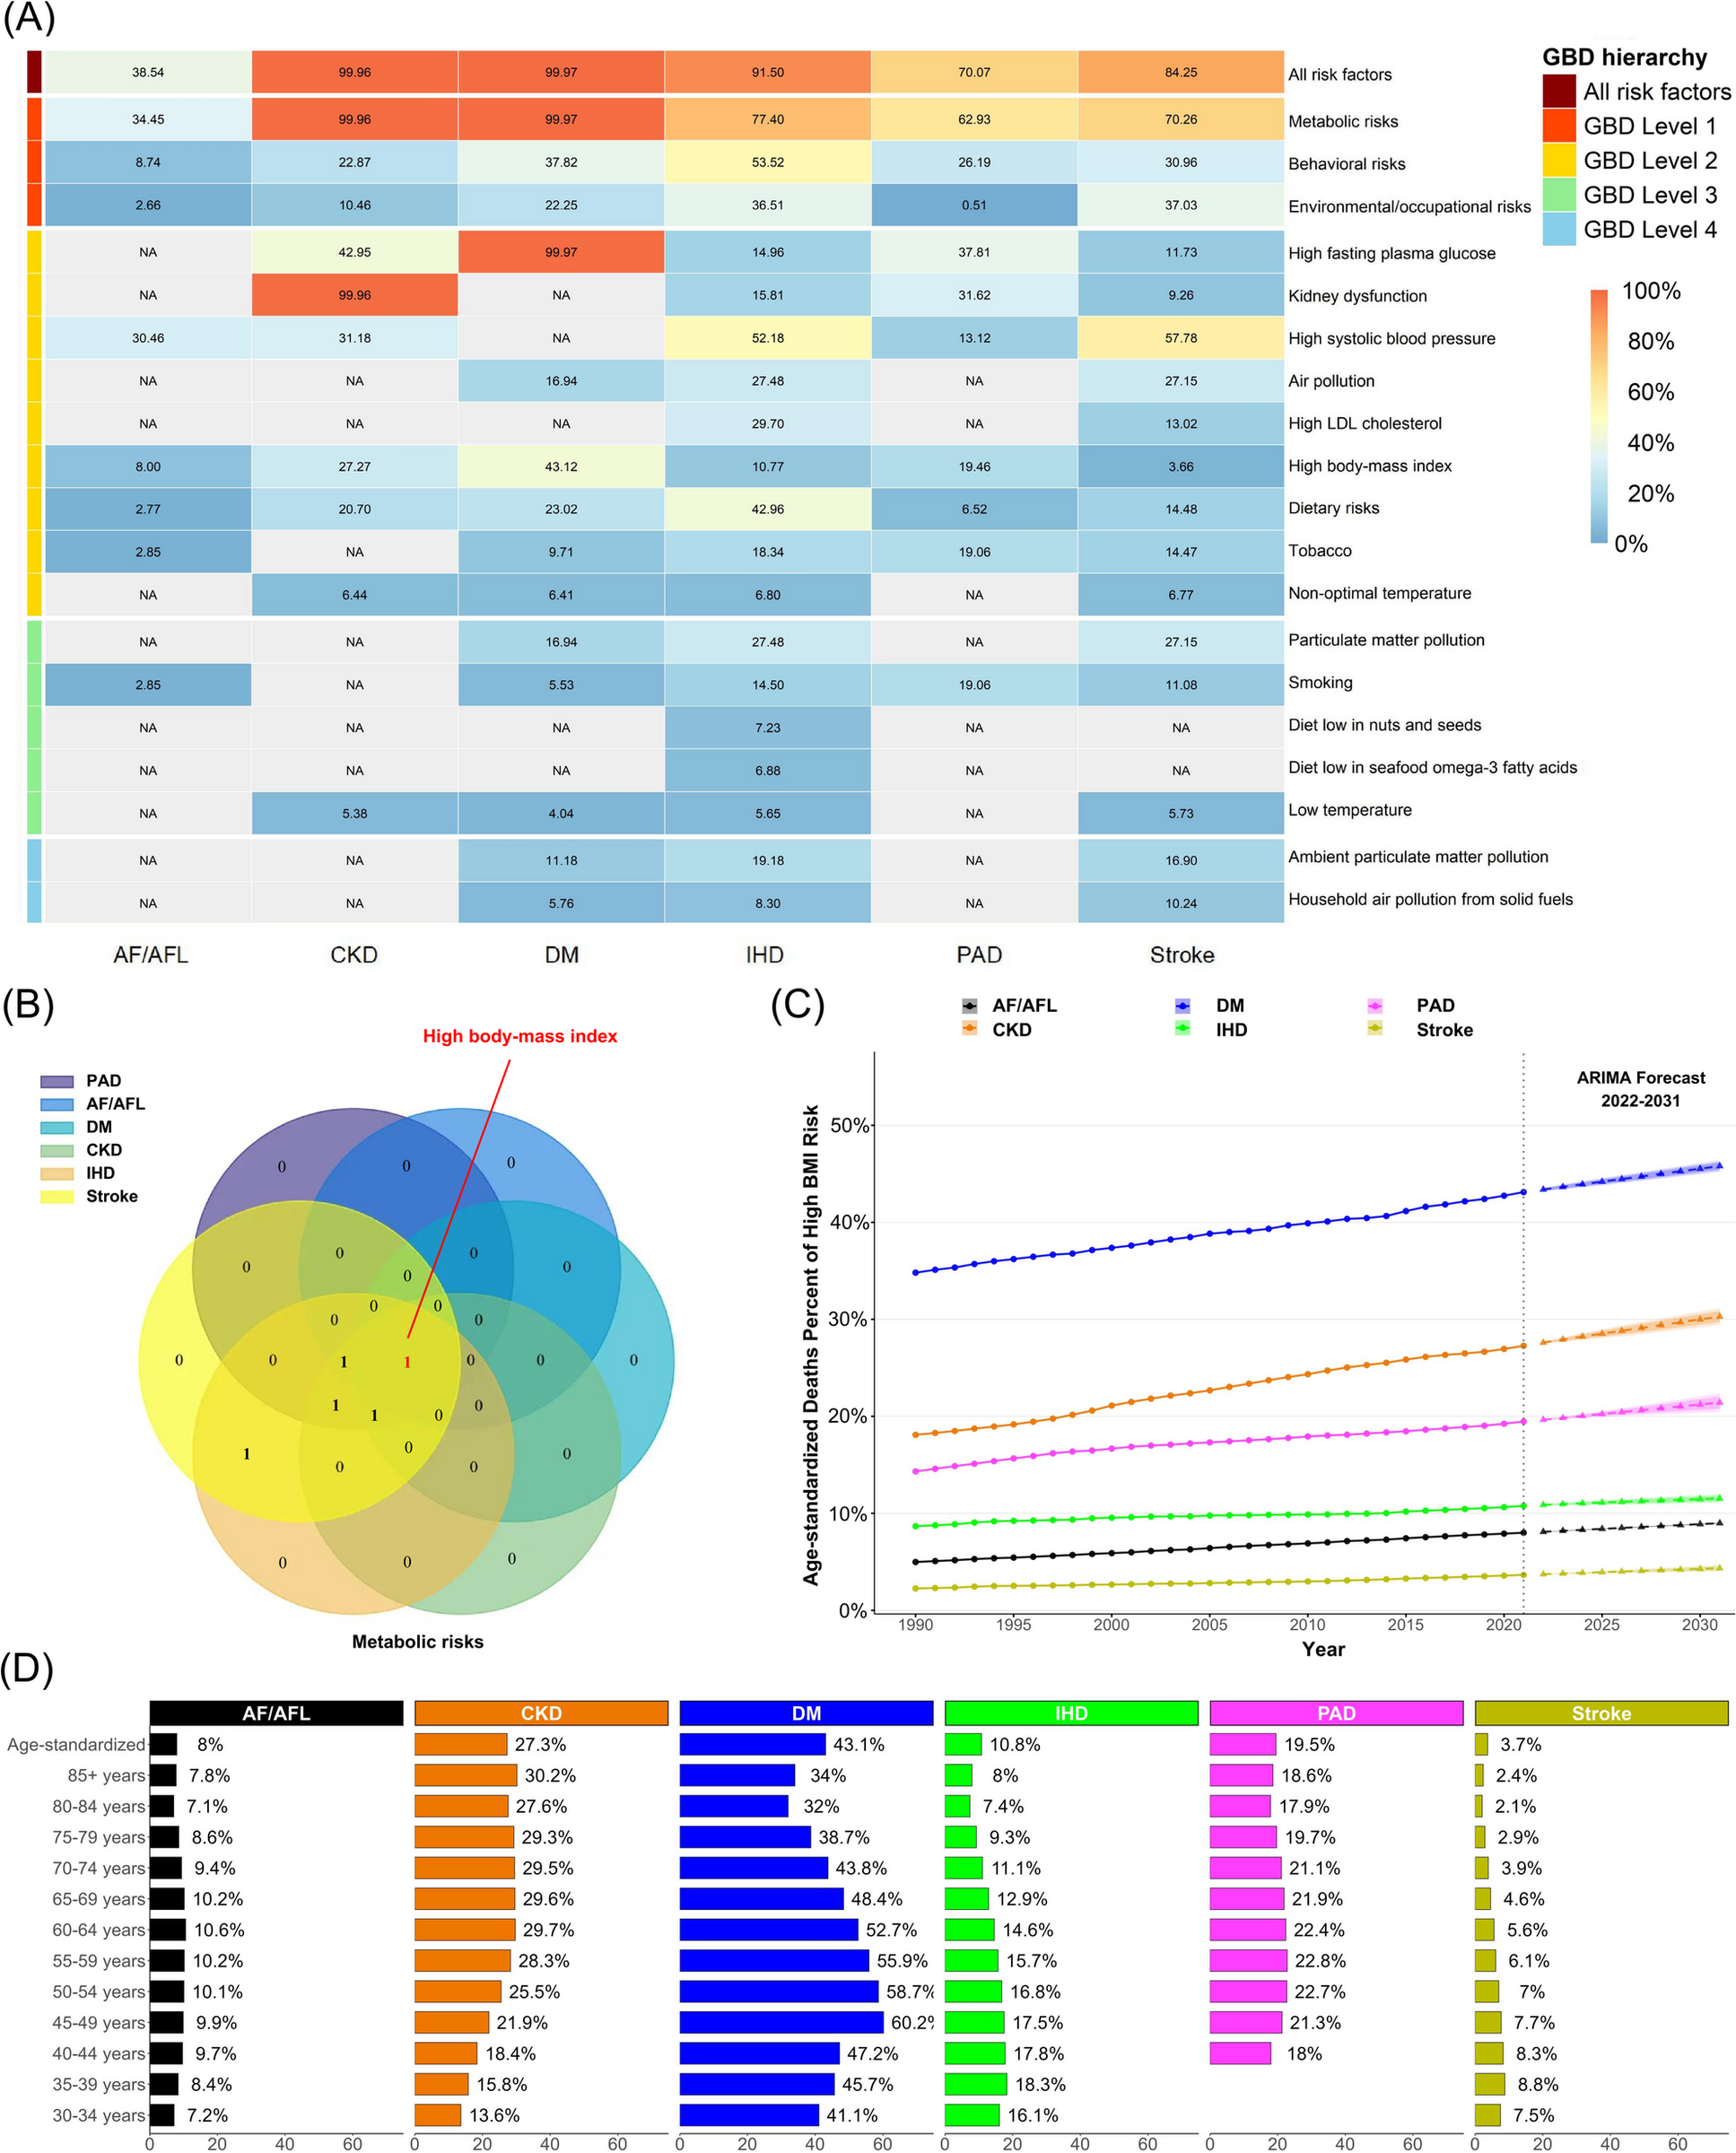
In both cohorts, mortality followed a broadly U-shaped pattern. The lowest point generally shifted toward higher body mass index as disease stage advanced. In UK Biobank, however, a genetic score indicating susceptibility to higher body mass index showed an approximately linear association with higher mortality, without a survival advantage. A standard deviation measures how widely scores vary. The authors suggested that the apparent obesity paradox may partly reflect body mass index’s limitations as a measure of body fat, rather than a true protective effect of excess fat.
Why it matters
For assessing risk from age-related cardiovascular disease, the authors supported using measures of body fat beyond body mass index.
Caveats
Observational associations can be distorted by other health differences and by illness affecting weight. Genetic susceptibility is not the same as testing whether a weight-change intervention alters survival.
From the paper
- Result
Conversely, BMI-GRS showed approximately linear adverse associations with all-cause mortality (HR per 1-SD increment 1.05, 95% CI 1.04–1.06) and CVD mortality (HR 1.10, 95% CI 1.07–1.12), and mortality risk increased progressively with advancing CKM stage across BMI-GRS strata (P for trend < 0.001).
Quoted word for word from the full text on link.springer.com.
- Lipid and ceramide metabolism
- Obesity
- Body mass index
- Cardiovascular-kidney-metabolic syndrome
- Cardiovascular disease
- Humans
The paper
China-Japan Friendship Hospital; Capital Medical University
Cardiovascular Diabetology, Oct 27, 2026, Open access, CC BY-NC-ND