Lipoprotein(a) and long-term revascularization burden: a recurrent-event analysis of the UK Biobank
Abstract
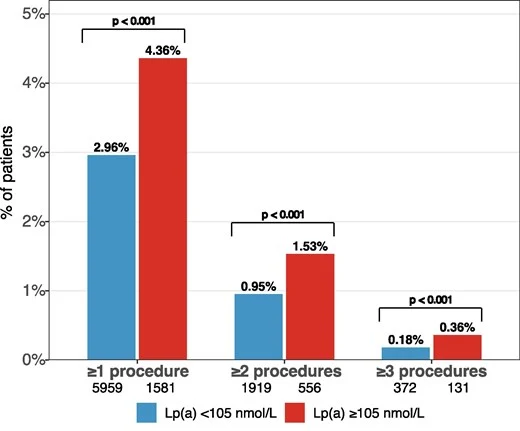
AIMS: To investigate whether elevated Lp(a) is independently associated with cumulative coronary, peripheral, and carotid revascularization burden in a primary prevention cohort. METHODS AND RESULTS: We analysed 237 729 UK Biobank participants of European ancestry free of ASCVD at baseline, followed for a median of 14.1 years. Lp(a) was analysed using the ESC/EAS 2025 threshold of 105 nmol/L and continuously (per 50 nmol/L increment). The primary outcome was the total number of coronary, peripheral, and carotid revascularization procedures per person. Given the genetically determined, lifelong nature of Lp(a) exposure, to capture the full sequence of procedures over time, rather than time-to-first-event alone, we applied recurrent-event statistical models, including the Andersen-Gill model, negative binomial regression, and the Prentice-Williams-Peterson gap-time model. Overall, 10 731 revascularization procedures occurred in 237 729 participants. The proportion undergoing ≥1 procedure was higher with Lp(a) ≥ 105 vs. <105 nmol/L (4.36% vs. 2.96%), with larger differences for ≥2 (1.53% vs. 0.95%) and ≥3 procedures (0.36% vs. 0.18%). In Andersen-Gill analysis, Lp(a) ≥ 105 nmol/L was associated with a higher revascularization rate (HR 1.50, 1.42-1.60), with a 55% higher rate of revascularization procedures during follow-up by negative binomial regression (IRR 1.55, 1.45-1.65). The association was strongest for the first procedure (HR 1.48, 1.40-1.56), attenuated for the second (HR 1.28, 1.09-1.50), and non-significant for the third (HR 1.23, 0.94-1.62). Findings were consistent across coronary and peripheral territories. CONCLUSION: In this large primary prevention cohort, elevated Lp(a) was independently associated with a higher long-term revascularization burden across multiple vascular territories. The association was robust for coronary, supportive for peripheral, and inconclusive for carotid revascularization owing to limited statistical power. These findings, derived from recurrent-event methodology, provide a more complete quantification of Lp(a)-associated cardiovascular procedural risk than time-to-first-event analyses alone.
From the paper
- Participants
The analytical cohort comprised 237 729 UK Biobank participants of European ancestry free of ASCVD at baseline, followed for a median of 14.1 years, contributing to a total of 3 306 828 person-years of follow-up.
- Follow-up
We analysed 237 729 UK Biobank participants of European ancestry free of ASCVD at baseline, followed for a median of 14.1 years.
- Result
A standard Cox model for time to first revascularization showed an HR of 1.48 (95% CI, 1.40–1.56), consistent with prior UK Biobank analyses11 (see Supplementary material online, Table S2).
- Absolute difference
The crude incidence rates were 0.465 and 0.303 per 100 person-years, respectively, yielding a crude IRR of 1.541 and an incidence rate difference of 0.161 per 100 person-years.
- Limitation
First, as an observational study, residual confounding cannot be excluded despite adjustment for major cardiovascular risk factors.
Quoted word for word from the full text on academic.oup.com.
The paper
University of Campania "Luigi Vanvitelli"; Karolinska University Hospital
European Journal of Preventive Cardiology, 14 Oct 2026, Open access