Association of 24 h Pulse Pressure Derived from Ambulatory Blood Pressure Monitoring with All-Cause and Cardiovascular Mortality in Patients Undergoing Peritoneal Dialysis: A Prospective Cohort Study
Abstract
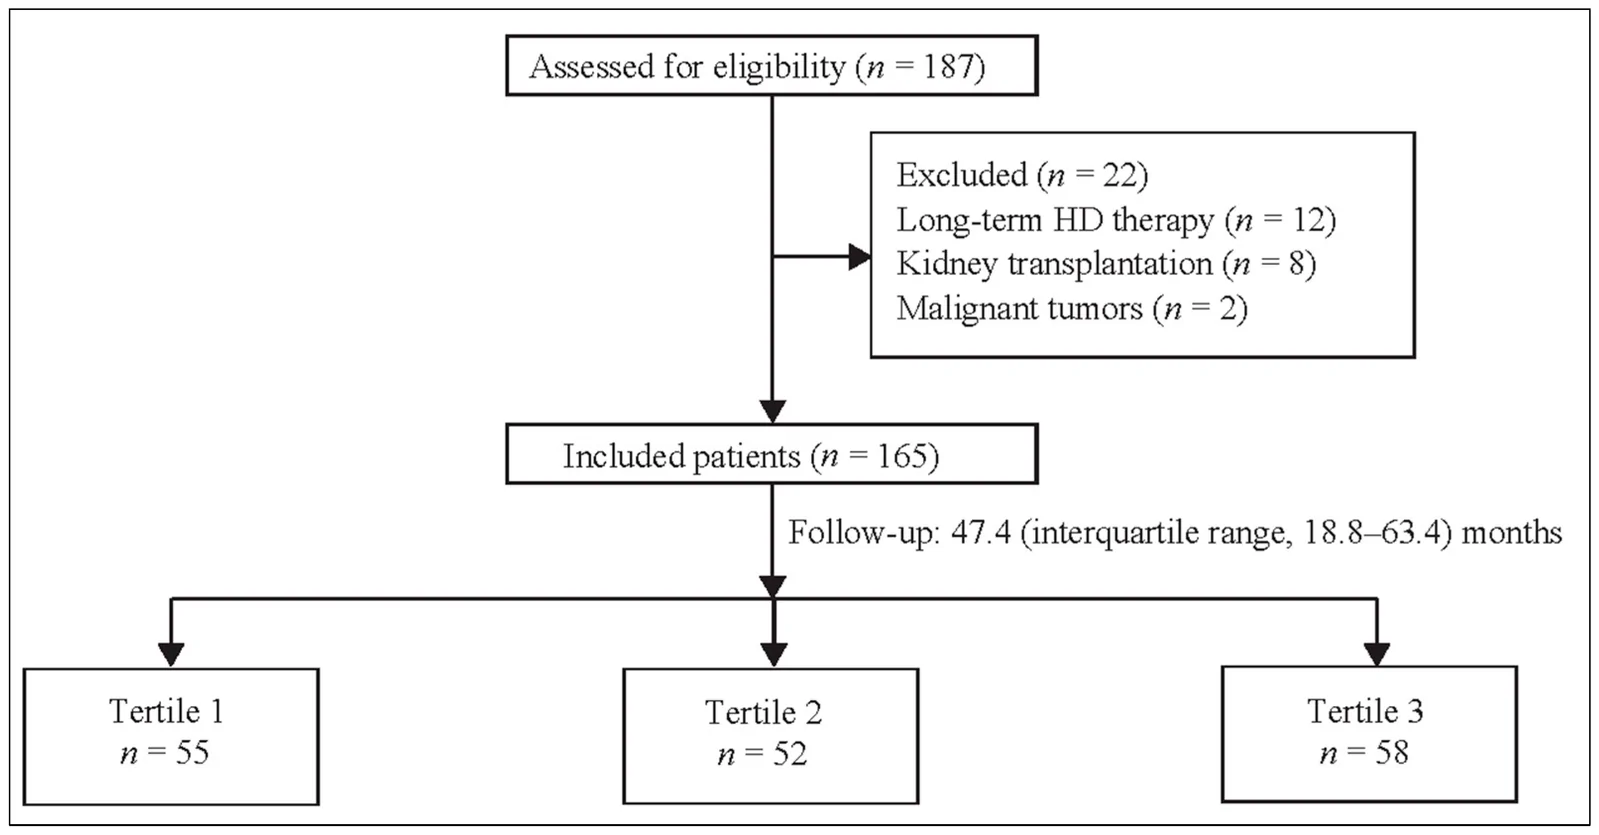
Background/Objectives: Pulse pressure (PP), an indirect hemodynamic marker reflecting the pulsatile component of blood pressure, has been linked to adverse outcomes in dialysis patients. Whether 24 h PP (24 h PP) derived from ambulatory BP monitoring (ABPM) is independently associated with all-cause and cardiovascular (CV) mortality in peritoneal dialysis (PD) patients remains unclear. Methods: This sub-cohort, nested within a single-center prospective PD database, enrolled 165 patients with baseline 24 h ABPM. The 24 h PP was analyzed continuously and in tertiles. All-cause mortality was assessed by Cox regression and CV mortality by Fine-Gray competing-risk modeling. The median follow-up was 47.4 months, counted from the date of ABPM completion. Results: During follow-up, 48 patients (29.1%) died, including 28 CV deaths (58.3% of all deaths). Per 1-SD increment in 24 h PP, the adjusted hazard ratio (HR) for all-cause mortality was 1.39 (95% confidence interval [CI] 1.03-1.87; p = 0.032), and the adjusted subdistribution hazard ratio (SHR) for CV mortality was 1.44 (95% CI 1.06-1.94; p = 0.018). The highest tertile showed elevated risks of all-cause (HR 3.47; 95% CI 1.12-10.70; p = 0.031) and CV mortality (SHR 5.11; 95% CI 1.32-19.79; p = 0.018) versus the lowest, persisting after adjustment for office PP. Conclusions: Elevated ABPM-derived 24 h PP is independently associated with increased all-cause and CV mortality in PD patients after adjustment for office PP.
The paper
The First Affiliated Hospital, Sun Yat-sen University
Journal of Clinical Medicine, 29 Sep 2026, Open access