Financial incentives raise quit rates in underserved adults
Six-month sustained abstinence reached 8.8% with incentives plus free medication, versus 4.3% with usual care and 5.1% with usual care plus free medication.
6 months, multicentre, registered NCT04798664, declared ties to: Pfizer, Viatris, American Thoracic Society and 7 more
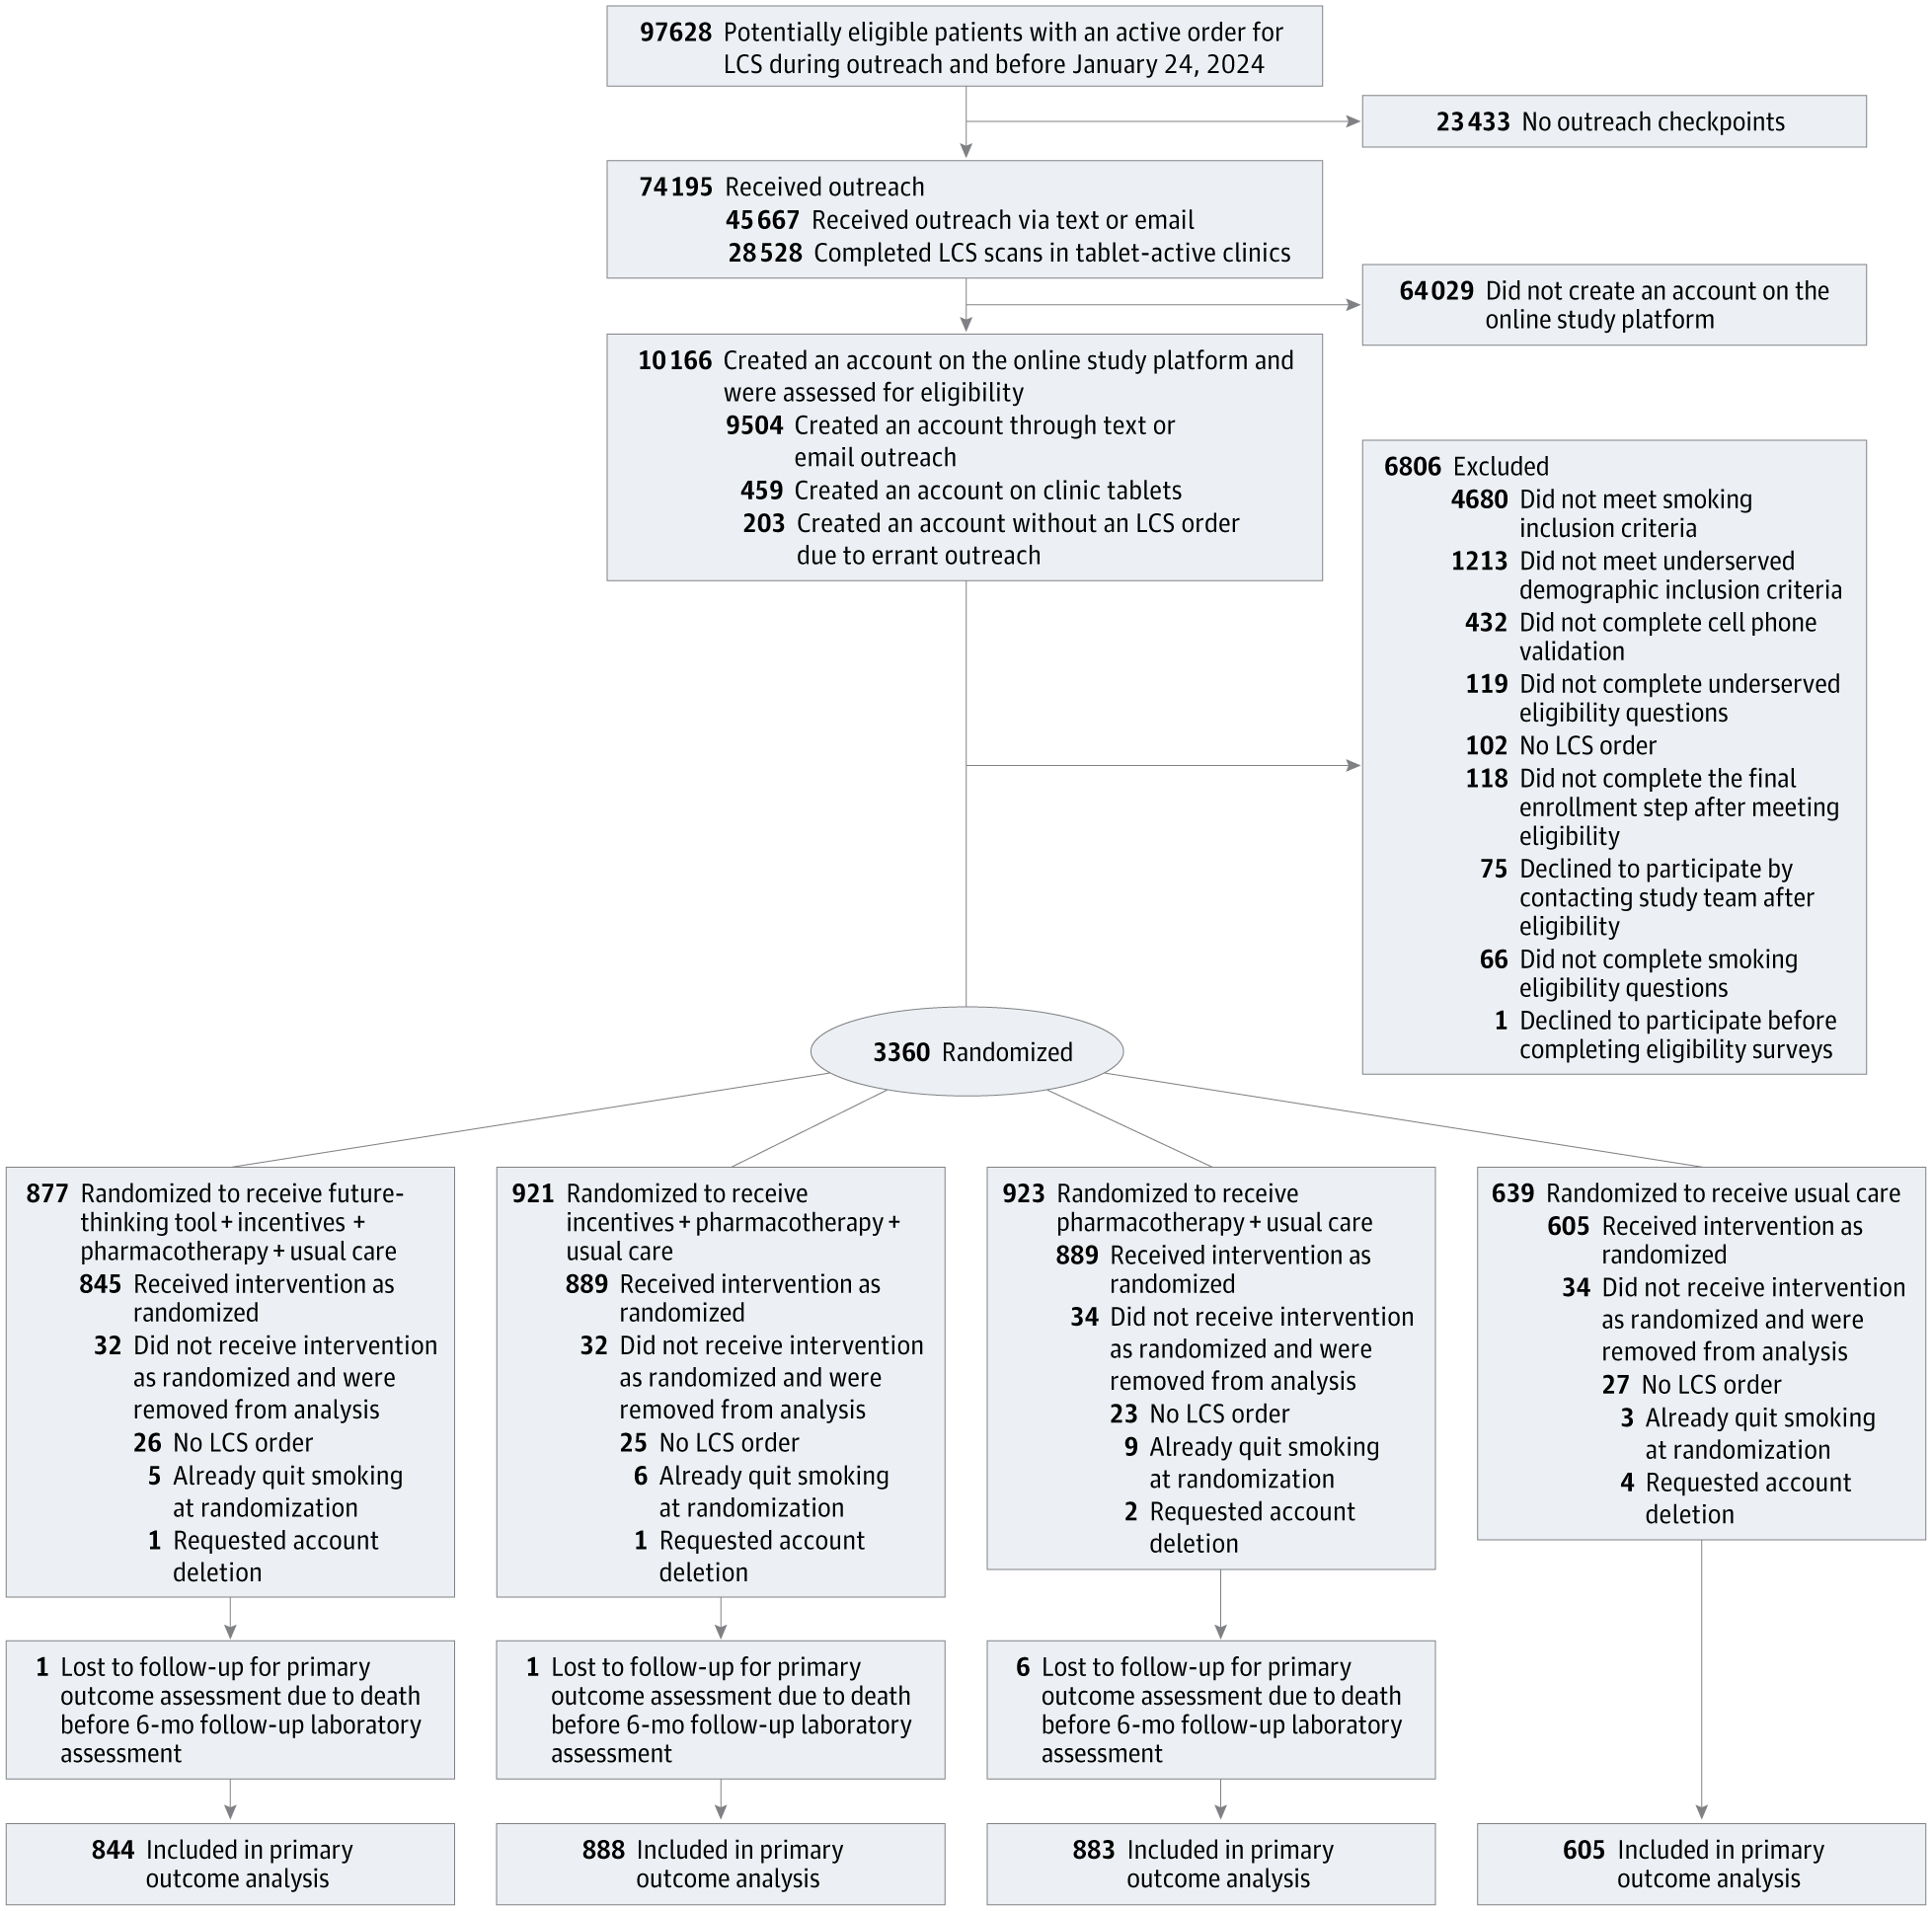
Among medically underserved adults who smoked and were referred for lung cancer screening, a randomized trial found higher sustained quit rates when financial incentives accompanied usual care and free medication. Researchers randomized 3,259 participants at five centers across four US health systems; 3,220 entered the primary analysis. Median age was 61.1 years.
Usual care involved asking about smoking, advising cessation and referring patients to cessation services. Other groups added free medication, then incentives of up to $600, or both plus a mobile tool focused on future health. Abstinence required biochemical confirmation through six months. Incentives increased the adjusted abstinence rate by 4.6 percentage points versus usual care and 4.1 percentage points versus usual care plus medication. Adding medication without incentives was not superior to usual care. The mobile-tool group had a 7.2% abstinence rate.
Why it matters
The trial supports financial incentives as a cessation strategy in an underserved screening population. It did not assess effects on biological aging or longevity.
Caveats
The primary outcome covered only six months, so longer-term abstinence remains uncertain. The trial focused on medically underserved adults referred for lung cancer screening.