Histopathological and immunohistochemical analyses do not indicate timing of prophylactic hysterectomy: a retrospective analysis of endometrial biopsies in Lynch syndrome carriers
Abstract
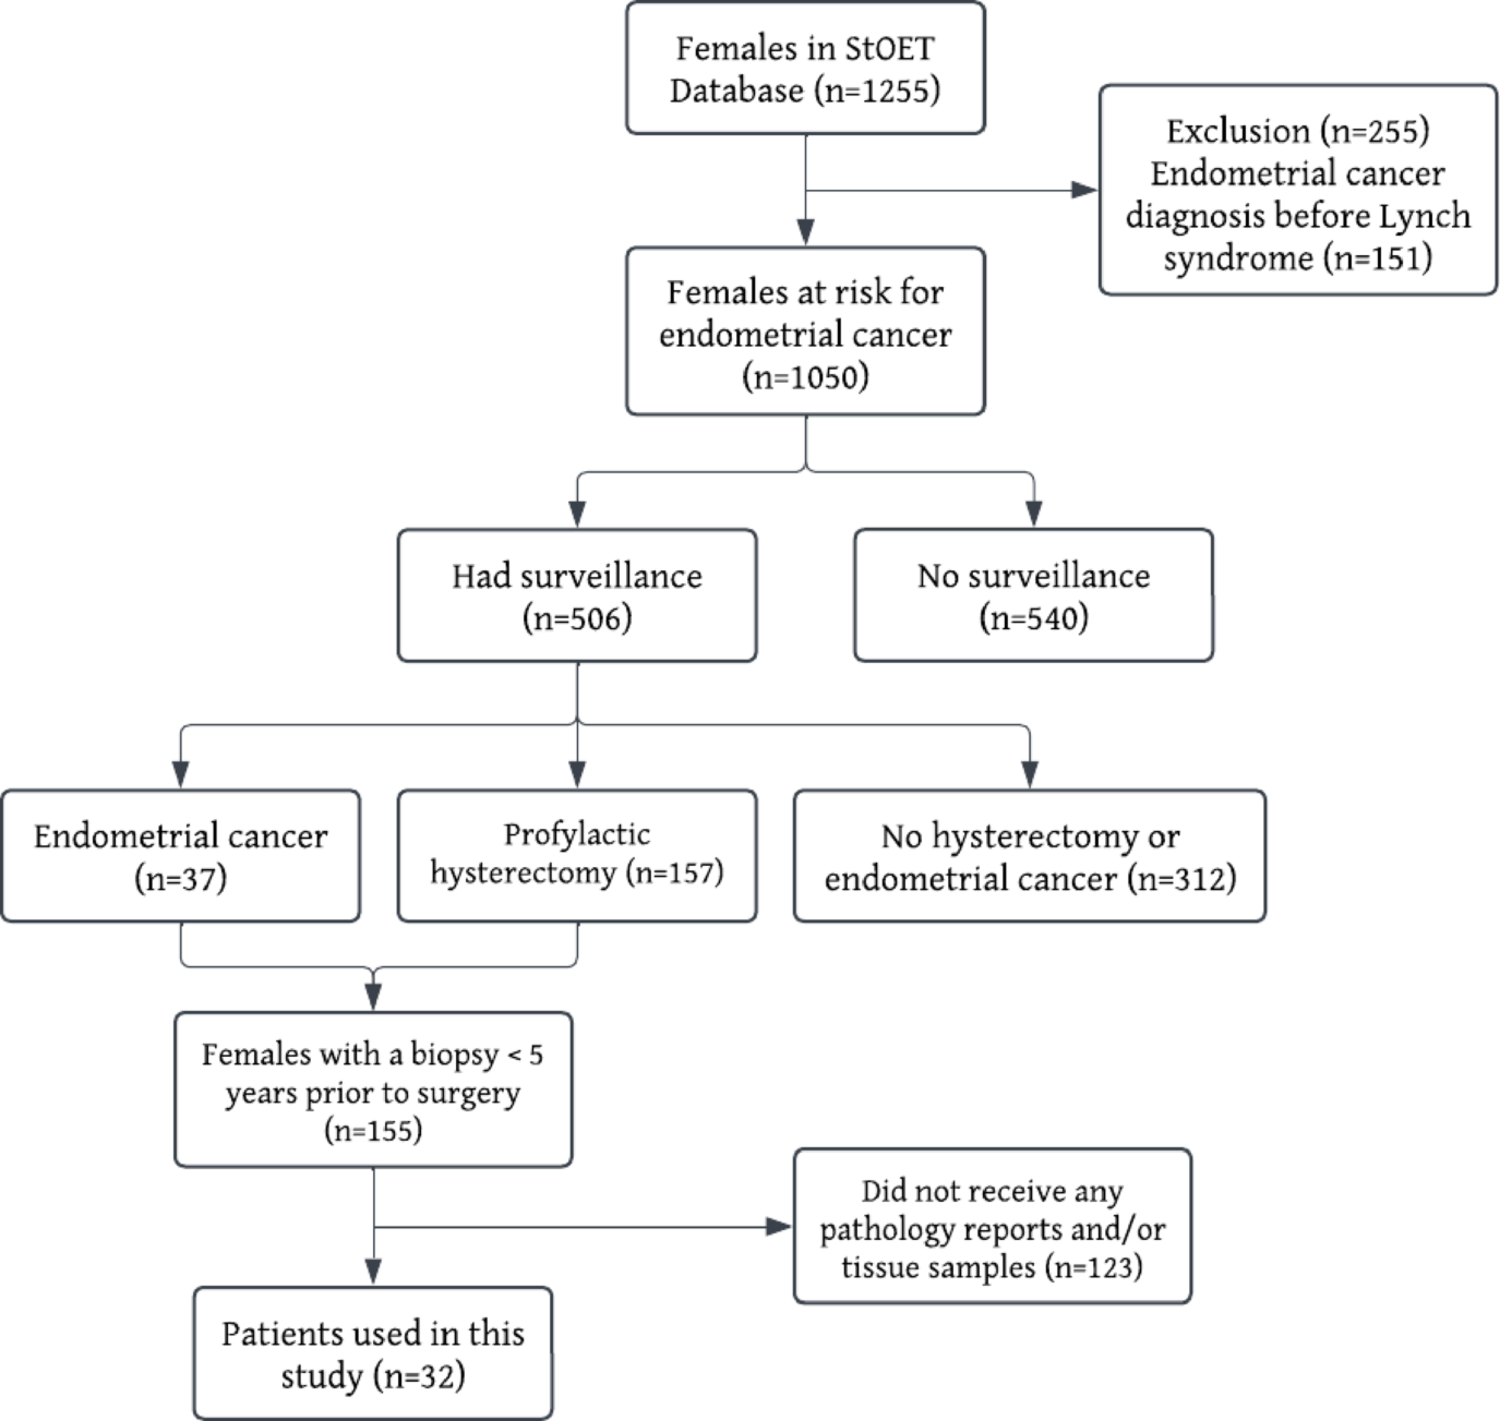
Women with Lynch syndrome are at increased risk of endometrial cancer. Gynecological surveillance is advised, but also prophylactic hysterectomy is an option. This study aimed to gain more insight in tumorigenesis in Lynch carriers to be able to personalize prophylactic hysterectomy timing. To this aim endometrial cancer surveillance in Lynch syndrome carriers was assessed using data from the Dutch Lynch syndrome database linked to the Dutch National Pathology Databank (PALGA). Eligible participants were Lynch syndrome carriers under surveillance, who underwent hysterectomy and had ≥ 1 endometrial biopsy within five years prior to surgery. Pathology reports, describing the histopathological features of the samples, were collected and, if available, samples were revised by a specialized pathologist. Additionally loss of expression of ARID1A, PTEN, PAX2, and mismatch repair (MMR) proteins was studied. Pathology reports from 32 Lynch syndrome carriers were analyzed: 16 had normal endometrium at hysterectomy, five had hyperplasia without atypia, six had endometrial intra-epithelial neoplasia (EIN), and five had endometrial cancer. Prior to hysterectomy, hyperplasia with or without atypia or endometrial cancer was reported in 3% of biopsies in the histopathological normal group, 26% in endometrial hyperplasia without atypia group, 26% in the EIN group, and 36% in the endometrial cancer group. Upon revision, combined neoplastic development of tissue and loss of protein expression were observed in 12% of the normal group, 36% of endometrial hyperplasia without atypia, 36% of EIN, and 50% of endometrial cancer group. So, increasing tissue disorganization and loss of protein expression appeared to correlate with progression to (pre)malignancy. However, no specific marker or consistent pattern emerged that could guide clinical decisions on prophylactic hysterectomy for individual patients. These findings highlight the complexity of endometrial cancer development in Lynch syndrome and underscore the need for further research to improve surveillance strategies and optimize timing of prophylactic surgery.
The paper
University Medical Center Rotterdam
Familial Cancer, 15 Oct 2026



