Machine learning-based screening for Ascertain Dementia 8-defined suspected cognitive impairment leveraging routine health check data in South China
Abstract
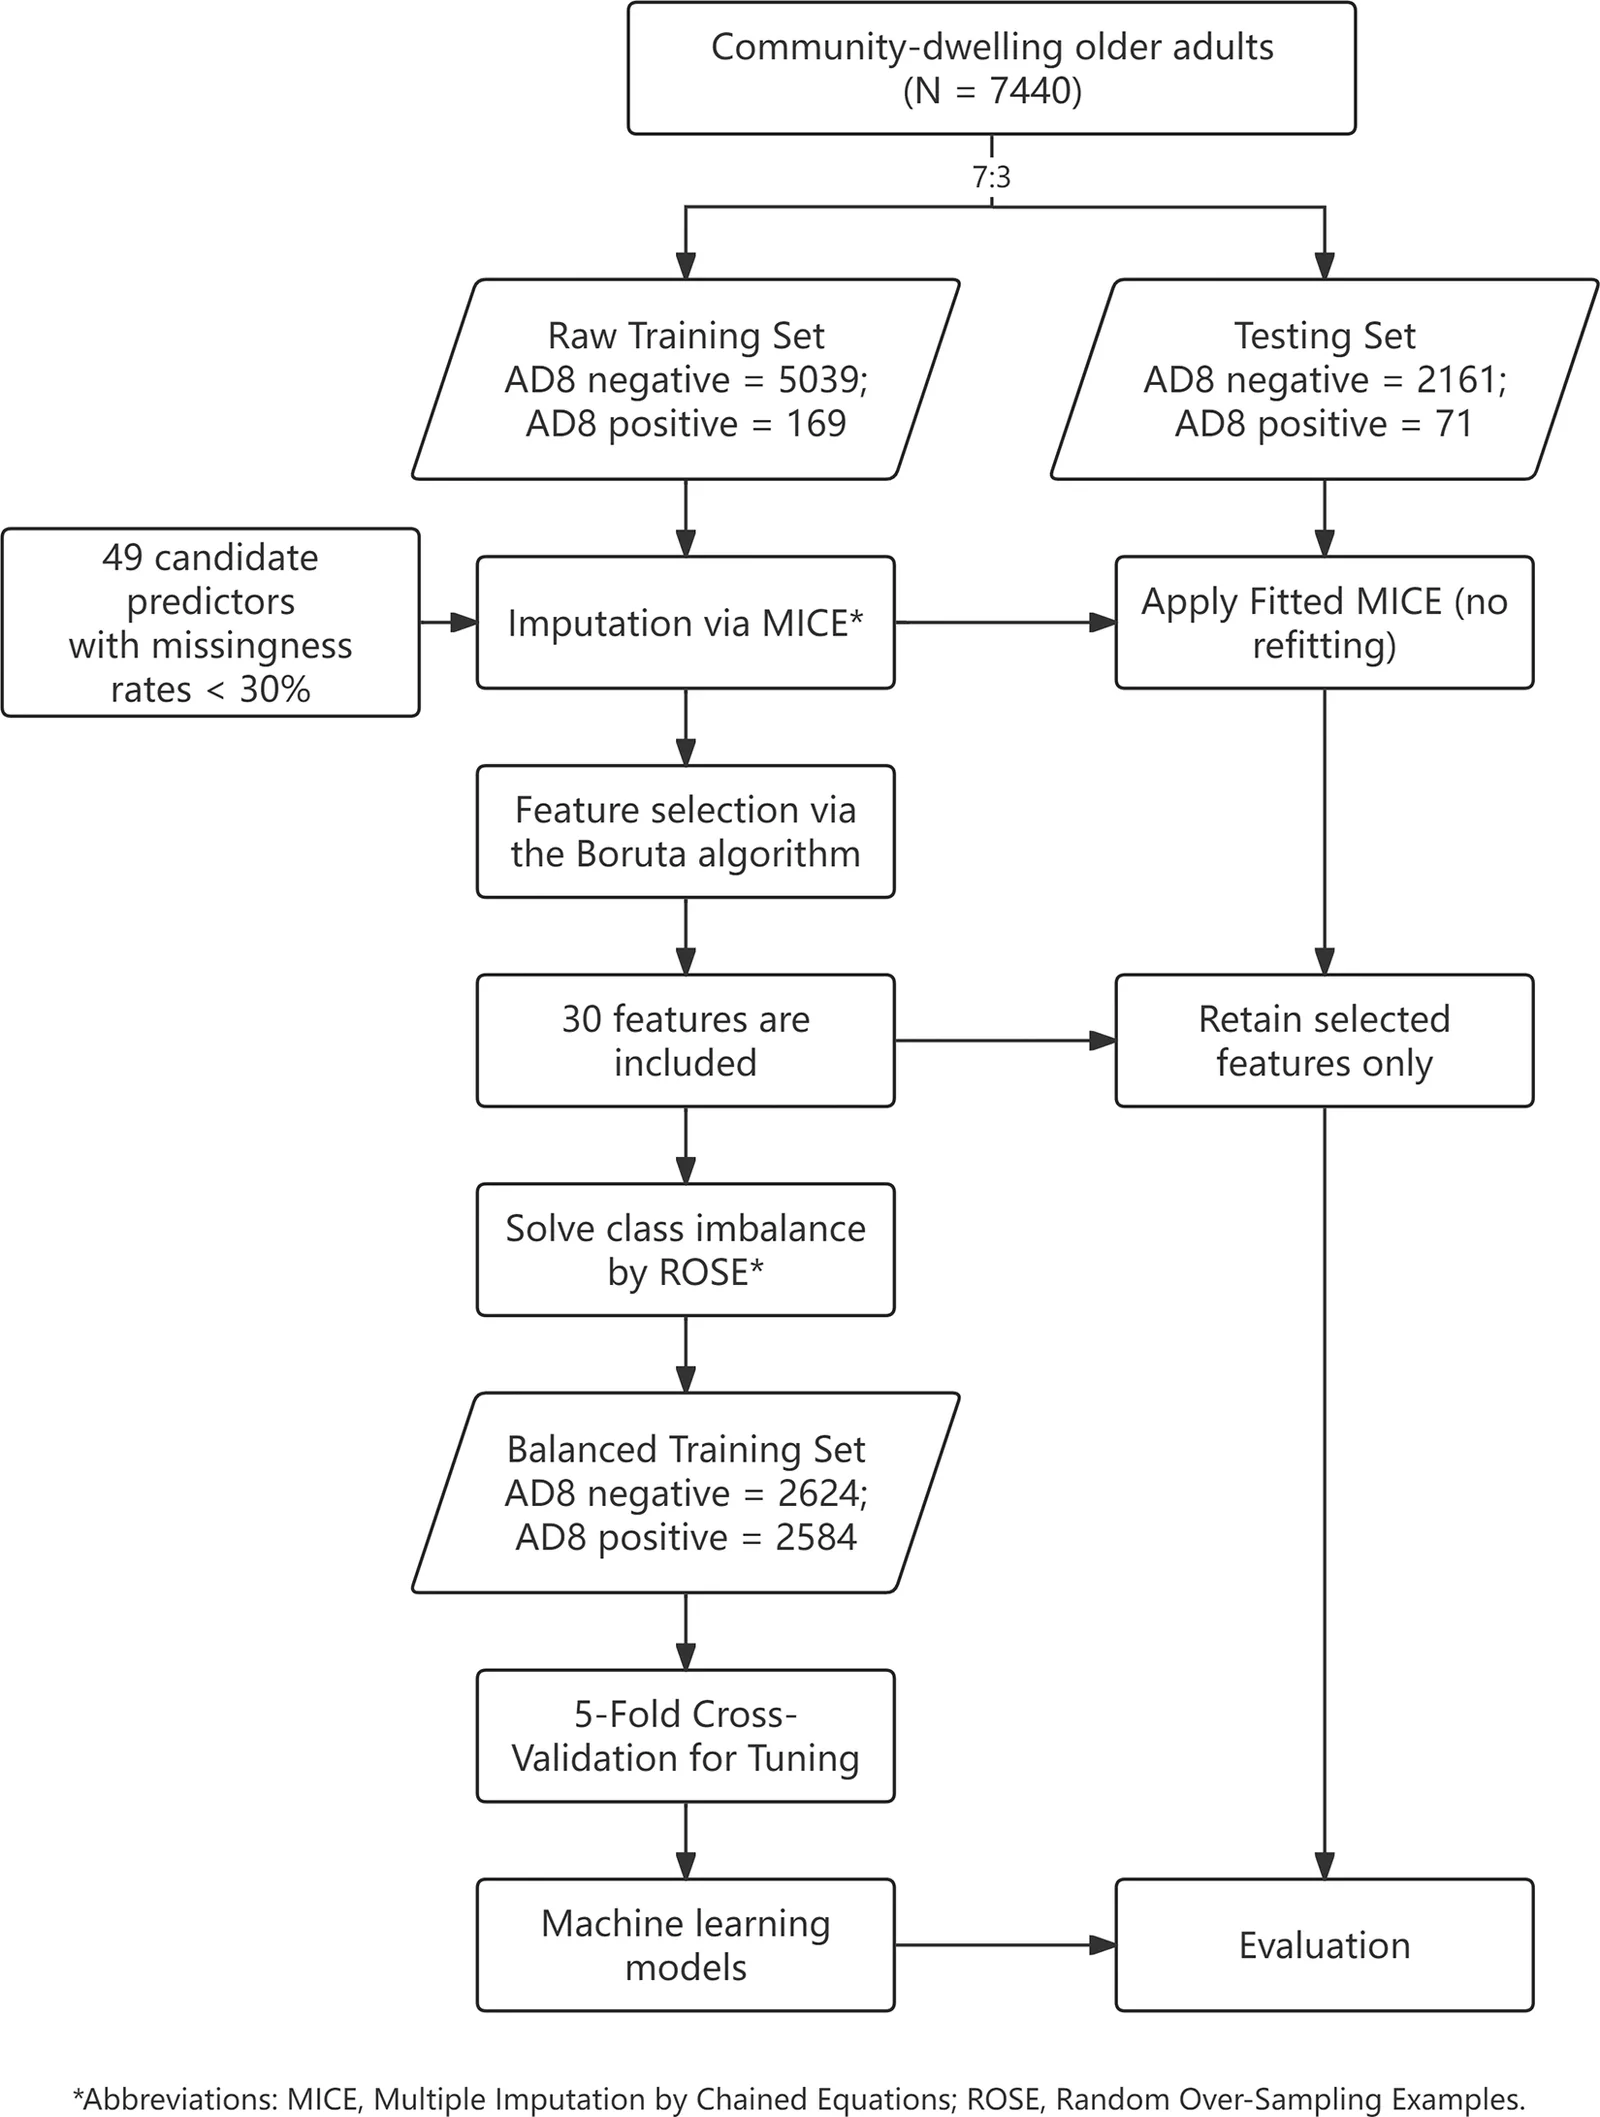
BACKGROUND: Timely detection of cognitive concerns can facilitate further assessment, referral, and management; however, cognitive impairment often remains under-detected in primary care settings, representing a missed opportunity for early detection for Alzheimer's disease and related dementias. OBJECTIVE: We aimed to develop and internally validate a machine learning-based cross-sectional concurrent classification model that utilizes routine health check data only, supporting concurrent identification of individuals with Ascertain Dementia 8 (AD8)-defined suspected cognitive impairment who warrant further clinical cognitive evaluation. METHODS: This cross-sectional study included 7440 adults (aged ≥65 years) from the 2021 Elderly Health Check Program in Shenzhen, China. Suspected cognitive impairment was defined as an AD8 score ≥2. Following data splitting, feature selection was processed via the Boruta algorithm. Five algorithms-logistic regression, random forest, XGBoost, SVM, and EasyEnsemble-were evaluated. Performance was assessed using ROC, PR, accuracy, sensitivity, specificity, PPV, NPV, NNS, DCA, calibration plots, and Brier score. RESULTS: The EasyEnsemble model outperformed other algorithms on the independent testing set, with an ROC-AUC of 0.696 (Bootstrap-corrected mean: 0.677; 95% CI: 0.643-0.713). At the clinically optimized threshold of 0.034, the model achieved a sensitivity of 60.6%, a specificity of 73.4% and a NNS of 51.9. DCA indicated a positive net benefit across a threshold range approximately from 0.03 to 0.20, suggesting potential clinical utility for triage in this setting. CONCLUSIONS: This cross-sectional model provides a pragmatic, low-cost tool for concurrent case-finding of individuals with AD8-defined suspected cognitive impairment in primary care. However, further external validation in diverse geographic regions is mandatory before clinical implementation.
The paper
Sun Yat-sen University
Journal of Alzheimer's Disease Reports, 21 Jul 2026, Open access