"Baseline Characteristics and Utilization of Medical Therapies in Acute Hospitalized and Chronic Heart Failure Patients Enrolled in GRASP-HF: Differences Between ICARe-HF and Non-ICARe-HF Centres"
Multicentre
Abstract
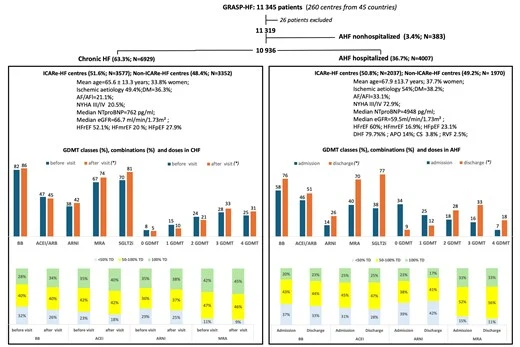
BACKGROUND: The Global Registries and Surveys Programme-Heart Failure (GRASP-HF) is a prospective, multicentre, international observational study assessing implementation of the 2021/2023 ESC-HF-Guidelines. GRASP-HF is aligned with the Improving Care through Accreditation and Recognition in Heart Failure (ICARe-HF) programme, which links centre-characteristics with guideline-implementation performance. AIMS: To compare baseline characteristics, guideline-directed-medical-therapy (GDMT) implementation, and in-hospital outcomes between GRASP-HF patients managed in centres participating or not participating in the ICARe-HF programme. METHODS: GRASP-HF patients were stratified by ICARe-HF participation, clinical settings, acute (AHF) vs chronic HF (CHF) and ejection fraction (EF) subtypes. Hierarchical multivariable logistic regression models evaluated associations with quadruple therapy implementation and in-hospital mortality. RESULTS: Among 10,936 patients (63.3% CHF, 36.7% AHF), patients from ICARe-HF participating centres (51.3%) were older, more comorbid but with less severe congestion. In both CHF and AHF, ICARe-HF centres demonstrated greater GDMT utilization, particularly angiotensin receptor-neprilysin inhibitors and sodium-glucose-cotransporter-2 inhibitors. In HFrEF, quadruple therapy was more frequently implemented (47% vs 40% in CHF; 27% vs 24% at AHF discharge) and remained associated with ICARe-HF participation after adjustment, Odd Ratio (OR) =1.73, 95% Confidence Interval (CI) :1.17-2.55. Target doses remained suboptimal, particularly after AHF. Although crude in-hospital mortality was lower in ICARe-HF centres (2.3% vs 5.5%), this association was attenuated after multivariable adjustment (OR=0.87, 95% CI:0.48-1.56). CONCLUSIONS: Participation in the ICARe-HF programme was associated with more comprehensive implementation of contemporary GDMT, particularly in HFrEF. The association with in-hospital mortality was attenuated after adjustment and should be considered exploratory.
- Angiotensin receptor-neprilysin inhibitor
- Guideline-directed medical therapy
- MME
- SLC5A2
- Chronic heart failure
- Humans
The paper
University of Medicine and Pharmacy 'Carol Davila'
European Journal of Heart Failure, 13 Oct 2026